Prescription required. We facilitate access to medicines already prescribed by your treating physician. We do not provide medical advice or diagnoses.


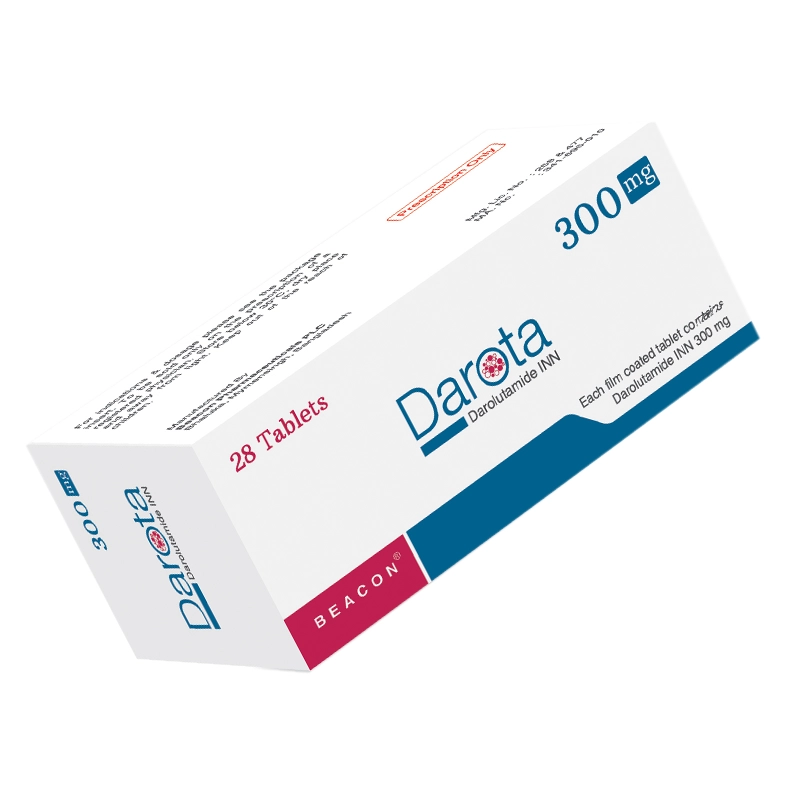
Darota 300mg (Darolutamide)
- Used for: Targeted oncology therapy.
- Availability: In Stock
- Shipping: Express Global Shipping (7-14 days depending on region).
- Requirement: Valid prescription from a licensed healthcare provider required.
✓ WHO GMP Certified
✓ Reviewed By Medical Expert
✓ Batch Examined in Lab
Need Patient Access Support?
Our team provides verified global sourcing assistance to help you navigate international shipping and prescription requirements safely.
What our medical expert told about Darolutamide
“Darolutamide is an androgen receptor inhibitor I consider for men whose prostate cancer still responds to hormone therapy, and for men with a rising PSA after castration but no visible metastases. It is always given alongside ongoing androgen deprivation therapy. In the pivotal trials, adverse reactions such as fatigue and rash were mostly mild, and seizures were rare. Before starting, I want a confirmed diagnosis with up-to-date imaging, a PSA doubling time for non-metastatic disease, and a full medication review. Darolutamide raises rosuvastatin levels about fivefold and should not be combined with strong enzyme inducers such as rifampin.”
Dr. Salma Mamdouh Elreedy, Clinical Oncologist, Sphinx Cure Oncology Center
Clinical Uses & Safety Management Protocols
Darota 300mg is a generic Nubeqa alternative containing darolutamide, manufactured by Beacon Pharmaceuticals PLC in Bangladesh. Darolutamide is a second-generation, nonsteroidal androgen receptor (AR) inhibitor. It blocks the receptor that testosterone and other androgens use to drive prostate cancer growth.
Darota is a prescription-only oncology medicine. It should be started and monitored by an oncologist or urologist experienced in treating prostate cancer.
Darolutamide is used in men with prostate cancer at two stages. The first is non-metastatic castration-resistant prostate cancer (nmCRPC), where PSA keeps rising despite androgen deprivation therapy (ADT) but scans show no spread. The second is metastatic castration-sensitive prostate cancer (mCSPC), where the cancer has spread but still responds to hormone therapy. In mCSPC it can be given alone with ADT or together with docetaxel chemotherapy.
In every setting, patients continue ADT with a GnRH agonist or antagonist, unless they have had a bilateral orchiectomy. Darolutamide does not require a corticosteroid such as prednisone. Treatment continues until the disease progresses or side effects become unacceptable.
Precise Indications & Biomarker Necessity
The current US prescribing information (revised September 2026) lists darolutamide for the treatment of adult patients with three conditions.
Non-metastatic castration-resistant prostate cancer (nmCRPC). PSA is rising despite castrate testosterone levels on ADT, and conventional imaging (CT, MRI, bone scan) shows no distant metastases. The ARAMIS trial enrolled men with a PSA doubling time of 10 months or less, the group at highest risk of developing metastases.
Metastatic castration-sensitive prostate cancer (mCSPC). Approved in June 2025 based on ARANOTE, which included both high-volume and low-volume metastatic disease. Darolutamide is given with ADT and no chemotherapy.
mCSPC in combination with docetaxel. Based on ARASENS. Darolutamide is started first, and the first of six docetaxel cycles should begin within 6 weeks. ARASENS excluded men whose only spread was to regional lymph nodes.
Tests needed before starting. Darolutamide does not require a genomic biomarker. The prescriber confirms the stage with imaging, a baseline PSA, a testosterone level confirming castration (for nmCRPC), and a PSA doubling time for nmCRPC. A cardiac risk review is also advisable, given the label’s ischemic heart disease warning.
The Nubeqa label contains no separate limitation-of-use statement.
Mechanism & Pharmacokinetics (ADME)
Mechanism of action. Darolutamide competitively inhibits androgen binding to the androgen receptor, blocks AR nuclear translocation, and blocks AR-mediated transcription. Its main metabolite, ketodarolutamide, showed similar activity in laboratory studies. Together these steps shut down the androgen signal that prostate cancer cells depend on, which slows tumor growth. Darolutamide is also a weak progesterone receptor antagonist, at about 1% of its AR activity.
Its chemical structure differs from enzalutamide and apalutamide. In a rat study presented at ASCO GU 2018, darolutamide showed much lower brain penetration than enzalutamide. This is preclinical data, and no trial has compared the drugs head to head in patients.
Absorption. Peak plasma levels are reached about 4 hours after a single 600 mg dose. Absolute bioavailability is about 30% when fasting. Taking darolutamide with food raises bioavailability 2.0- to 2.5-fold, which is why the label says to take every dose with food. Steady state is reached 2-5 days after repeated dosing with food, with about 2-fold accumulation.
Distribution. The apparent volume of distribution after IV dosing is 119 L. Protein binding is 92% for darolutamide and 99.8% for ketodarolutamide, mainly to serum albumin.
Metabolism. Darolutamide is metabolized mainly by CYP3A4, and also by UGT1A9 and UGT1A1. Total plasma exposure to ketodarolutamide is about 1.7 times that of darolutamide.
Elimination. The effective half-life of darolutamide and ketodarolutamide is about 20 hours. After a radiolabeled dose, about 63% was recovered in urine (about 7% unchanged) and about 32% in feces (about 30% unchanged), with over 95% recovered within 7 days.
Dosage & Adverse Event (AE) Management
Starting dose. 600 mg (two 300 mg tablets) by mouth twice daily with food, for a total of 1,200 mg a day. Tablets are swallowed whole. Patients continue a GnRH agonist or antagonist unless they have had a bilateral orchiectomy. With docetaxel, the first of six docetaxel cycles starts within 6 weeks of starting darolutamide.
Dose reduction. For a Grade 3 or higher adverse reaction, or one the patient cannot tolerate, the prescriber withholds darolutamide or reduces it to 300 mg twice daily until symptoms improve. Treatment can return to 600 mg twice daily once the reaction is back to baseline. The label does not recommend going below 300 mg twice daily.
Discontinuation triggers. Stop darolutamide for Grade 3-4 ischemic heart disease. Consider stopping it in patients who have a seizure.
Strength availability. Every label dose (600 mg and 300 mg twice daily) can be given with the 300 mg tablet, so Darota has no strength gap.
Renal impairment. Severe (eGFR 15-29 mL/min/1.73 m², not on hemodialysis): 300 mg twice daily. Mild or moderate: no dose change. End-stage renal disease has not been studied.
Hepatic impairment. Moderate (Child-Pugh B): 300 mg twice daily. Mild: no dose change. Severe (Child-Pugh C) has not been studied.
Adverse reactions in the pivotal trials. Each trial’s table uses its own reporting threshold, shown below as the label states it.
| Trial (setting) | Label threshold | Adverse reactions, darolutamide vs placebo |
|---|---|---|
| ARAMIS (nmCRPC) | >2% with a ≥2% increase over placebo | Fatigue 16% vs 11%; pain in extremity 6% vs 3%; rash 4% vs 1.4% |
| ARAMIS (nmCRPC), lab tests | as listed in the label | AST increased 23% vs 14%; neutrophil count decreased 20% vs 9%; bilirubin increased 16% vs 7% |
| ARANOTE (mCSPC) | ≥10% with a ≥2% increase over placebo | Urinary tract infection 12% vs 8% |
| ARANOTE (mCSPC), lab tests | >15% with a ≥5% increase over placebo | AST increased 32% vs 25%; ALT increased 28% vs 23%; bilirubin increased 17% vs 7%; neutrophil count decreased 16% vs 9% |
| ARASENS (mCSPC with docetaxel) | ≥10% with a ≥2% increase over placebo with docetaxel | Constipation 23% vs 20%; rash 20% vs 15%; decreased appetite 19% vs 13%; hemorrhage 18% vs 13%; weight increased 18% vs 16%; hypertension 14% vs 10% |
Serious and fatal adverse reactions. In ARAMIS, serious adverse reactions occurred in 25% of patients on darolutamide vs 20% on placebo, and fatal reactions in 3.9% vs 3.2%. In ARANOTE, serious reactions occurred in 24% and fatal reactions in 4.7%. In ARASENS, with docetaxel, serious reactions occurred in 45% (febrile neutropenia 6%) and fatal reactions in 4%.
Discontinuation and dose changes. Adverse reactions led to permanent discontinuation in 9% (ARAMIS), 6% (ARANOTE) and 14% (ARASENS). Dose reductions were needed in 6%, 3.6% and 9%, respectively.
Drug-Drug Interaction (DDI) Matrix
Darolutamide is cleared mainly by CYP3A4 and is a P-gp substrate, and it inhibits the BCRP, OATP1B1 and OATP1B3 transporters. A full medication review, including herbal products, is needed before starting Darota.
| Interacting agent class | Examples | Effect on darolutamide or the other drug | Recommended action |
|---|---|---|---|
| Combined P-gp and strong or moderate CYP3A4 inducers | Rifampin (studied); carbamazepine, phenytoin, St. John’s wort | Rifampin lowered darolutamide AUC by 72% and Cmax by 52%; moderate inducers are expected to lower exposure by 36-58% | Avoid the combination; it may reduce darolutamide’s effect |
| Combined P-gp and strong CYP3A4 inhibitors | Itraconazole (studied); ketoconazole, clarithromycin | Itraconazole raised darolutamide AUC 1.7-fold and Cmax 1.4-fold | Monitor more often for darolutamide side effects and adjust the dose as needed |
| BCRP substrates | Rosuvastatin, sulfasalazine, methotrexate | Higher levels of the other drug | Avoid where possible; if used, monitor more often and consider lowering the other drug’s dose per its label |
| OATP1B1 and OATP1B3 substrates | Rosuvastatin, atorvastatin, pitavastatin | Higher levels of the other drug | Monitor more often and consider lowering the other drug’s dose per its label |
| Rosuvastatin (BCRP, OATP1B1 and OATP1B3 substrate) | Rosuvastatin | Rosuvastatin AUC and Cmax rose about 5-fold | Review the statin choice and dose with the prescriber |
| CYP3A4 substrates | Midazolam (studied) | Midazolam AUC fell 29% and Cmax 32% | No clinically relevant effect per the label |
| P-gp substrates | Dabigatran (studied) | No clinically relevant change | No action needed per the label |
| Docetaxel | Docetaxel 75 mg/m² | No clinically relevant change in either drug | Used together in mCSPC per the ARASENS regimen |
| Food | Any meal | Bioavailability up 2.0- to 2.5-fold | Take every dose with food |
The label names drug classes only. The examples other than the studied drugs are common members of each class; the prescriber or pharmacist should check each medicine individually.
Clinical Efficacy & Real-World Data
Three randomized, double-blind phase 3 trials support darolutamide. The figures below are from Section 14 of the current US label.
ARAMIS (nmCRPC). 1,509 men with non-metastatic CRPC and a PSA doubling time of 10 months or less were randomized 2:1 to darolutamide or placebo, both with ADT. Median metastasis-free survival, the primary endpoint, was 40.4 months vs 18.4 months (HR 0.41; 95% CI 0.34-0.50; p<0.0001). Darolutamide also improved overall survival (HR 0.69; 95% CI 0.53-0.88; p=0.003), with deaths in 15% vs 19% of patients. Time to pain progression (HR 0.65) and time to cytotoxic chemotherapy (HR 0.58) were also longer.
ARASENS (mCSPC with docetaxel). 1,306 men were randomized 1:1 to darolutamide or placebo, each with ADT and six cycles of docetaxel. Overall survival, the primary endpoint, improved with darolutamide (HR 0.68; 95% CI 0.57-0.80; one-sided p<0.0001). Median OS was not reached with darolutamide vs 48.9 months with placebo, and deaths occurred in 35% vs 46%.
ARANOTE (mCSPC without docetaxel). 669 men with high- or low-volume metastatic disease were randomized 2:1 to darolutamide or placebo, both with ADT. Radiographic progression-free survival improved (HR 0.54; 95% CI 0.41-0.71; p<0.0001). The placebo median was 25 months, and the darolutamide median was not reached.
Caveat. In ARANOTE, the overall survival difference (HR 0.78; 95% CI 0.58-1.05) was not statistically significant at the final analysis. The survival benefit shown in ARASENS applies to darolutamide given with docetaxel.
No phase 3 trial has compared darolutamide head to head with enzalutamide, apalutamide or abiraterone for survival.
Darota vs Abiraxen vs Prostaxen
All three are oral hormone therapies taken with ongoing ADT, but they work differently and follow different food and steroid rules. Data are from each originator’s current US label.
| Feature | Darota (darolutamide) | Abiraxen (abiraterone acetate) | Prostaxen (apalutamide) |
|---|---|---|---|
| Originator | Nubeqa | Zytiga | Erleada |
| Mechanism | AR inhibitor | CYP17 inhibitor (blocks androgen production) | AR inhibitor |
| Standard dose | 600 mg twice daily | 1,000 mg once daily | 240 mg once daily |
| Food rule | With food | Empty stomach: no food 2 hours before and 1 hour after | With or without food |
| Steroid needed | No | Yes, prednisone 5 mg (twice daily in mCRPC, once daily in mCSPC) | No |
| US-approved settings | nmCRPC; mCSPC; mCSPC with docetaxel | Metastatic CRPC; metastatic high-risk CSPC | nmCRPC; mCSPC |
| Seizure risk in label | 0.2% (pooled ARAMIS and ARANOTE); stop to be considered | No seizure warning | 0.4%; stop permanently |
| Key label warnings | Ischemic heart disease, seizure | Mineralocorticoid excess (low potassium, fluid retention), hepatotoxicity | Cerebrovascular and ischemic cardiovascular events, falls and fractures, seizure |
| Bangladeshi manufacturer | Beacon | Everest | Everest |
Darolutamide is the only one of the three approved for both nmCRPC and use alongside docetaxel in mCSPC. Abiraterone is the only one that needs a daily steroid and a fasting window.
Precautions & Special Populations
Ischemic heart disease: Ischemic heart disease, including fatal cases, occurred in patients taking darolutamide. In pooled ARAMIS and ARANOTE data it occurred in 3.4% vs 2.2% on placebo (Grade 3-4: 1.4% vs 0.3%). In ARASENS it occurred in 3.2% with docetaxel vs 2% on placebo with docetaxel. Patients should be monitored for chest pain and other signs, with cardiovascular risk factors such as high blood pressure, diabetes and high cholesterol managed alongside treatment. Darolutamide is stopped for Grade 3-4 events.
Seizure: Grade 1-3 seizures occurred in 0.2% of patients in pooled ARAMIS and ARANOTE data, and in 0.8% in ARASENS (including two Grade 3 events). Patients with a seizure history should tell their oncologist. Stopping darolutamide should be considered if a seizure occurs during treatment.
Embryo-fetal toxicity: Darolutamide can cause fetal harm and loss of pregnancy. Men with female partners of reproductive potential must use effective contraception during treatment and for 1 week after the last dose. Animal studies suggest darolutamide may impair male fertility.
Lactation: No data exist on darolutamide in human milk. Darolutamide is indicated for men only.
Renal impairment: Severe impairment (eGFR 15-29 mL/min/1.73 m², not on hemodialysis) raises exposure, so the dose is 300 mg twice daily. Mild and moderate impairment need no change. End-stage renal disease has not been studied.
Hepatic impairment: Moderate impairment (Child-Pugh B) needs 300 mg twice daily. Mild impairment needs no change. Severe impairment (Child-Pugh C) has not been studied. Trial lab data showed more frequent rises in AST, ALT and bilirubin with darolutamide than with placebo.
Elderly patients: Most trial participants were 65 or older. No overall differences in safety or effectiveness were seen compared with younger patients.
Children: Safety and effectiveness have not been established in pediatric patients.
Global Access Guide and Quality Assurance
Darota is manufactured by Beacon Pharmaceuticals PLC, a WHO-GMP certified Bangladeshi manufacturer. A facility’s WHO-GMP certification confirms the manufacturing process meets international quality standards. It is not the same as FDA approval of this generic product. Darota is supplied for personal import under Named Patient Program frameworks where legally permitted; it is not FDA-approved.
Bioequivalence status. Darolutamide is a small molecule, so a bioequivalence comparison with Nubeqa is possible in principle. Beacon has not yet supplied comparative dissolution or bioequivalence data for Darota, so this page makes no bioequivalence claim. We will update this section if the data are provided.
Batch documentation. Each shipment is supplied with batch number, expiry date. Patients and their physicians can request these documents before ordering.
Storage. Do not store above 25°C temperature.. For reference, Nubeqa is stored at 20°C to 25°C (68°F to 77°F), with excursions permitted between 15°C and 30°C.
Beacon Pharmaceuticals PLC Manufacturing Insights
Beacon Pharmaceuticals PLC is a Dhaka-based manufacturer with a dedicated oncology portfolio, including targeted therapies such as Dasanix (dasatinib), Sunitix (sunitinib) and Bortez (bortezomib).
Global Access via Named Patient Program (NPP)
Patients outside Bangladesh can access Darota through Named Patient Program and personal-import pathways where their country’s regulations allow it. The process runs in four steps.
- Upload the prescription. Send a valid prescription from a licensed oncologist or urologist through the Upload Prescription page, or by WhatsApp (+8801792288474) or email (info@genericoncology.com).
- Receive a quote. Our team confirms stock, pack quantity and delivery timeline, and sends a written quote.
- Complete the documentation. We prepare the import documents your country requires, such as the prescription, invoice and batch documents. Some countries also need a permit or letter from the treating physician.
- Shipping with tracking. Darota is dispatched by express courier with a tracking number, typically arriving in 7-14 days depending on region.
Import rules vary by country. Patients should confirm with their physician and local regulator that personal import of darolutamide is permitted before ordering.
Darota 300mg vs Nubeqa 300mg (Head-to-Head Comparison)
| Feature | Darota 300mg | Nubeqa 300mg |
|---|---|---|
| Active ingredient | Darolutamide 300 mg | Darolutamide 300 mg |
| Dosage form | Oral tablet | Oral film-coated tablet |
| Strengths available | 300 mg (pack of 28 tablets) | 300 mg |
| Approved indications | Per Beacon: nmCRPC and metastatic hormone-sensitive prostate cancer | US label: nmCRPC; mCSPC; mCSPC with docetaxel |
| Dose | 600 mg twice daily with food (label dose) | 600 mg twice daily with food |
| Manufacturer | Beacon Pharmaceuticals PLC, Bangladesh | Bayer |
| Regulatory status | WHO-GMP certified facility; not FDA-approved; supplied under NPP frameworks | FDA-approved (nmCRPC 2019; mCSPC with docetaxel 2022; mCSPC 2025) |
| Bioequivalence data | Not yet supplied by Beacon | Reference product |
| Storage | Do not store above 25°C temperature. Keep away from light and wet place. Keep out of reach of children. | 20°C to 25°C |
Both contain the same active ingredient at the same strength, and the dosing schedule is the same. The differences are the manufacturer, the regulatory pathway and the bioequivalence data still to come from Beacon.
Frequently Asked Question
Is Darota the same medicine as Nubeqa?
Both contain darolutamide 300 mg and use the same dose of 600 mg twice daily. Darota is made by Beacon Pharmaceuticals PLC in a WHO-GMP certified facility, while Nubeqa is made by Bayer and is FDA-approved. Darota is not FDA-approved, and Beacon has not yet supplied bioequivalence data.
How does darolutamide work?
It blocks the androgen receptor, the switch that testosterone uses to drive prostate cancer growth. It is always taken with ongoing androgen deprivation therapy, which lowers testosterone itself.
Do I need a test before starting Darota?
No genomic biomarker test is required. Your doctor confirms the stage of disease with imaging and PSA, checks that testosterone is at castrate level, and measures PSA doubling time for non-metastatic disease.
Should Darota be taken with food?
Yes. Take two tablets twice a day with food, swallowed whole. Food raises the amount of darolutamide absorbed 2.0- to 2.5-fold.
How long does one pack last?
One pack holds 28 tablets. At the standard dose of four tablets a day, a pack lasts 7 days, so a month of treatment needs about four packs.
What should I do if I miss a dose?
Take the missed dose as soon as you remember, up to the time of your next scheduled dose. The label allows the missed dose to be taken together with the next scheduled dose if needed. Then continue your normal twice-daily schedule.
When should I call my doctor?
Call right away for chest pain or pressure, shortness of breath, or a seizure. Also report rash, unusual tiredness, signs of a urinary tract infection, or bleeding.
Can darolutamide be used after enzalutamide, apalutamide or abiraterone stops working?
The label’s indications do not include use after progression on another androgen receptor pathway inhibitor. Your oncologist will choose the next treatment based on imaging, PSA and, often, genetic testing of the tumor.