Prescription required. We facilitate access to medicines already prescribed by your treating physician. We do not provide medical advice or diagnoses.


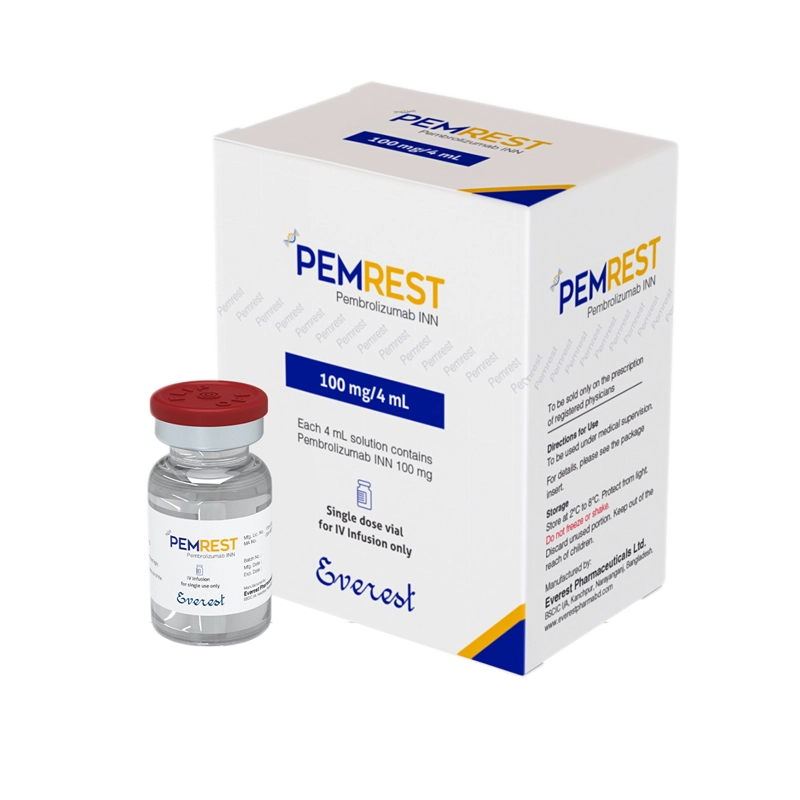
Pemrest 100 mg / 4 ml (Pembrolizumab) | Keytruda Alternative & Price Guide
Our team provides verified global sourcing assistance to help you navigate international shipping and prescription requirements safely.
✓ WHO GMP Certified
✓ Reviewed By Medical Expert
✓ Batch Examined in Lab
Need Patient Access Support?
Description
Pemrest is an intravenous immunotherapy containing pembrolizumab, the same active molecule sold under the brand name Keytruda. Everest Pharmaceuticals manufactures it in Bangladesh under WHO-GMP standards, supplied as a 100mg/4mL single-dose vial.
Pembrolizumab does not attack tumor cells directly. It works on the immune system instead. Cancer cells frequently exploit a receptor called PD-1, which signals nearby T-cells to stand down and leave the tumor alone. Pembrolizumab blocks that signal, and T-cells that could already recognize the cancer are free to act on it again.
The drug is also unusual in how some of its approvals are written. For certain patients, eligibility depends on the tumor’s genetic profile (MSI-High or mismatch repair deficient status) rather than the organ where the cancer began. This was among the first tumor-agnostic approvals in oncology, and it explains why pembrolizumab’s label spans so many different cancer types.
If you are researching Pemrest as an alternative to the originator brand, one point needs stating plainly. Pemrest is not an FDA-approved or EMA-approved biosimilar. No biosimilar pembrolizumab has been approved in either market, because Keytruda remains under patent protection there. Production of patent-protected biologics in Bangladesh is permitted under the WTO’s TRIPS exemption for least-developed countries. We publish this here rather than leave you to discover it later.
Clinical Expert Insight
“Most of my patients arrive knowing pembrolizumab as a lung cancer or melanoma drug. Fewer know it can be prescribed on the basis of a genetic testing result, whatever organ the cancer started in. For someone who has already worked through the standard lines of therapy, that difference matters a great deal.
The counterpart is vigilance. This drug does not act on the tumor. It acts on the immune system, and an activated immune system can turn on healthy tissue. I tell patients that a new symptom deserves a phone call even when it seems unconnected to their cancer, and even when the last infusion was months ago. Breathlessness. Diarrhea that will not settle. Unexplained exhaustion. Those calls are what let us intervene while the problem is still small.”
— Dr. Salma Mamdouh Elreedy, Clinical Oncologist, Sphinx Cure Oncology Center
Pemrest Uses and Clinical Safety Protocols
Precise Indications & Biomarkers
- Biomarker-selected solid tumors: certain non-small cell lung cancers (by PD-L1 Tumor Proportion Score), unresectable or metastatic melanoma, recurrent or metastatic head and neck squamous cell carcinoma, and selected gastric, cervical, hepatocellular, urothelial and Merkel cell carcinomas.
- Hematologic malignancies: classical Hodgkin lymphoma and primary mediastinal large B-cell lymphoma in the relapsed or refractory setting.
- Tumor-agnostic indication: any advanced solid tumor identified as MSI-High, mismatch repair deficient, or high tumor mutational burden, regardless of where the cancer originated.
- Testing requirements: confirmed biomarker testing precedes treatment for most indications. The specific test depends on which indication applies, and results are not interchangeable between them.
Mechanism of Action, Pharmacokinetics & Administration
Pembrolizumab binds the PD-1 receptor on T-cells and blocks both of its ligands, PD-L1 and PD-L2. T-cells already primed against the tumor remain active as a result.
The drug stays in the body a long time. Its terminal half-life is roughly 22 to 27 days, which is why infusions are scheduled three to six weeks apart rather than daily or weekly. The same property explains something patients are rarely warned about: an immune-related side effect can surface months after a final infusion.
Other pharmacokinetic characteristics that shape treatment:
- Absorption: administered intravenously and therefore fully available in the bloodstream immediately. There is no absorption phase.
- Distribution: volume of distribution at steady state is small, approximately 6 to 7.4 L, typical for a therapeutic antibody.
- Metabolism: cleared through the general protein breakdown pathways that handle every antibody in the body. Liver enzymes (CYP450) play no part in its clearance. Hepatic and renal impairment therefore have limited effect on exposure.
- Clearance: low, at approximately 0.2 L per day.
Administration. Pemrest is given as an intravenous infusion over roughly 30 minutes, at a hospital or infusion center, by staff trained to administer it. Standard adult dosing is 200mg every three weeks or 400mg every six weeks. Combination regimens with chemotherapy may follow a different schedule set by the treating team. There is no self-administration, no dose adjustment at home and no missed-dose rule to memorize, since the infusion center holds the schedule. Many protocols cap treatment at around 24 months in patients who are responding well, though your oncologist decides the endpoint in your case.
Adverse Event (AE) Management Table
Chemotherapy side effects tend to follow a pattern patients can anticipate: hair loss, low blood counts, nausea at predictable points in the cycle. Pembrolizumab behaves differently. Because the drug works by reactivating the immune system, the principal risk is that the immune system inflames healthy tissue. This can happen in the lungs, bowel, liver, thyroid, kidneys or skin, and it often develops before you would notice anything yourself. That is why your team will check liver enzymes, creatinine and thyroid function at the start of treatment and at intervals throughout it.
The protocols below reflect general prescribing guidance for PD-1 inhibitors. Your oncologist’s judgment governs actual management.
| Toxicity | Incidence | Threshold | Action |
|---|---|---|---|
| Pneumonitis | ~3.4% | Grade 2 | Withhold; corticosteroids |
| Grade 3–4 | Permanently discontinue | ||
| Colitis | ~1.7% | Grade 2–3 | Withhold; corticosteroids |
| Grade 4 | Permanently discontinue | ||
| Hepatitis | <1% | Grade 2 | Withhold |
| Grade 3–4 | Permanently discontinue | ||
| Hypothyroidism | ~8.5% | Any grade | Continue; hormone replacement |
| Nephritis | <1% | Grade 2 | Withhold |
| Grade 3–4 | Permanently discontinue | ||
| Severe skin reactions | <1% | Grade 3 | Withhold |
| Grade 4, SJS/TEN | Permanently discontinue | ||
| Infusion reactions | Uncommon | Grade 1–2 | Slow or stop infusion |
| Grade 3–4 | Permanently discontinue |
Table-01: Immune-Mediated Adverse Event Management
Across all categories, treatment resumes only once symptoms settle to Grade 1 or lower and corticosteroids taper to a low maintenance dose within approximately 12 weeks. Where that taper cannot be achieved, treatment is usually stopped permanently.
Clinical Efficacy: The KEYNOTE Benchmarks
- First-line NSCLC (KEYNOTE-024, NCT02142738). This Phase III trial compared pembrolizumab monotherapy against platinum-based chemotherapy in previously untreated patients with PD-L1 TPS of 50% or greater. Five-year follow-up data published in the Journal of Clinical Oncology in 2021 showed overall survival of approximately 32% at five years with pembrolizumab, against approximately 16% with chemotherapy. It was the first Phase III first-line immunotherapy trial in NSCLC to report five-year outcomes.
- Melanoma (KEYNOTE-006). Supported the original approval, demonstrating superior survival against ipilimumab in previously untreated advanced disease.
- Head and neck cancer (KEYNOTE-048). Supported approval in recurrent and metastatic HNSCC, both as monotherapy and combined with chemotherapy.
- Tumor-agnostic MSI-H/dMMR (KEYNOTE-158 and related studies). Supported the biomarker-based approval covering any solid tumor meeting the genetic criteria.
Pembrolizumab’s label covers more indications than any other product in our catalogue, and each approval rests on its own pivotal trial rather than shared data. The FDA approval history page lists them in full.
Interaction & Precaution Matrix
Pembrolizumab has no classic CYP450-mediated drug interactions, and no formal pharmacokinetic interaction studies have identified any. Several treatment-level interactions still matter clinically.
| Consideration | Clinical concern | Guidance |
|---|---|---|
| Chronic systemic corticosteroids or immunosuppressants before treatment | May blunt efficacy by suppressing the immune activity the drug depends on | Avoid unless medically necessary; physiologic replacement doses are generally acceptable |
| Live vaccines | Insufficient safety data during active PD-1 blockade | Avoid during treatment |
| Other checkpoint inhibitors or immunotherapy combinations | Combination regimens carry distinct and higher-rate toxicity profiles | Managed only under combination-specific protocols, not interchangeable with monotherapy dosing |
| Prior solid organ or allogeneic stem cell transplant | Reported risk of transplant rejection and graft-versus-host disease | Requires coordination between oncology and transplant teams before initiation |
Table-02: Treatment-Level Interaction Considerations
Precautions & Special Populations
- Pregnancy. Pembrolizumab can cause fetal harm based on its mechanism of action. Patients of reproductive potential should use effective contraception during treatment and for at least four months after the final dose.
- Lactation. It is not known whether pembrolizumab passes into breast milk. Breastfeeding is not recommended during treatment or for four months after the final dose.
- Hepatic and renal impairment. Mild to moderate impairment does not usually require a dose change, for the reason set out in the pharmacokinetics section above. Data in severe impairment remains limited, and these patients need closer monitoring.
- Prior transplant history. Requires a joint decision between the oncology and transplant teams before starting.
- Storage. Pemrest must be kept refrigerated at 2°C to 8°C for its entire journey. It must not be frozen or shaken. This is the only product in our catalogue carrying a continuous cold-chain requirement; everything else we ship tolerates room temperature.
Certified Quality & International Distribution
Pemrest (Everest) and Keytruda (Originator) Compared
The table below states only what can be verified today.
| Metric | Pemrest (Everest) | Keytruda (Originator) |
|---|---|---|
| Active substance | Pembrolizumab | Pembrolizumab |
| Regulatory status | WHO-GMP manufactured; not an FDA-approved or EMA-approved biosimilar | FDA-approved and EMA-approved originator biologic |
| Comparability data | N/A | Full KEYNOTE clinical development programme |
| Manufacturing | WHO-GMP certified facility, Bangladesh | GMP certified, multiple global sites |
Table-03: Product Comparison
Everest Pharmaceuticals Manufacturing
Everest Pharmaceuticals produces Pemrest in a WHO-GMP certified facility with dedicated biologics handling.
Global Access: Named Patient Program (NPP)
Patients in regions where Pemrest is not locally registered may still access it under Named Patient or personal-use importation rules.
- Prescription. A valid prescription and treatment summary from your treating oncologist.
- Documentation. A Letter of Medical Necessity and patient identification.
- Import permit. Our team handles the personal-use import permit application with your local drug authority.
- Logistics. Because Pemrest is a refrigerated biologic, shipment goes through cold-chain-verified couriers with continuous temperature monitoring rather than the standard timeline used for our oral medicines.
Frequently Asked Questions (FAQs)
Is there a generic or alternative to Keytruda?
Pembrolizumab is the active ingredient in Keytruda, and Pemrest contains that same molecule, manufactured by Everest Pharmaceuticals under WHO-GMP standards. It is not an FDA-approved or EMA-approved biosimilar. Whether it suits your situation depends on your regulatory environment and your oncologist’s assessment. That decision belongs with your treating physician, not with this page.
Is Pemrest the same as Keytruda?
Same active ingredient and same mechanism. The difference is regulatory status. Keytruda holds FDA and EMA approval. Pemrest has no biosimilar approval in those markets, because no application has been filed for a drug still under patent there. Ask your oncologist how that distinction affects your treatment plan.
What does Pemrest cost?
Pricing varies by region, and cold-chain shipping and import permit requirements affect the final figure. Send us your location on WhatsApp and we will give you a specific quote rather than a range that may not apply to you.
Can I take Pemrest at home like a tablet?
No. Some patients assume that medicine shipped to them arrives as a pill, so this is worth stating clearly. Pemrest is an infusion, given by trained clinical staff, every three to six weeks.
Why does this need cold-chain shipping when your other products do not?
Pembrolizumab is a protein-based antibody rather than a small-molecule tablet, and proteins degrade at room temperature. Refrigeration throughout transport is a requirement of the product, not an added precaution on our part.
My first scan after starting looked worse. Has the treatment failed?
Not necessarily. Immune cells moving into a tumor can make it appear larger on an early scan before it begins to shrink, a phenomenon called pseudoprogression. Oncologists generally confirm with a repeat scan before concluding that treatment is not working. This is a useful conversation to have with your team before your first scan rather than after it.
How do the side effects differ from chemotherapy?
Hair loss and transfusion-dependent low blood counts are far less likely than with cytotoxic chemotherapy. What replaces them is a need for regular blood testing, because immune-related problems in the thyroid, liver and kidneys often develop without symptoms you would notice on your own.
How long will I be on this treatment?
There is no single answer. It depends on your cancer type and how you respond. Many protocols stop at around two years in patients doing well, but your oncologist sets your endpoint.